
Cannula or needle for dermal fillers: compare comfort and bruising
A blunt cannula can mean fewer skin entry points, but it isn’t automatically the better choice for every filler placement. In a cannula vs needle comparison for dermal fillers, design is the key difference: a cannula is long and blunt, while a needle is short and sharp. Cannulas can reduce punctures and may mean less discomfort and bruising; needles allow precise placement.
Both instruments have a role in dermal filler treatment. The choice depends on the treatment area, where the filler needs to sit and how it should be distributed. A cannula is inserted through an entry point made with a needle, then guided beneath the skin from that access point.
This guide explains how the instruments differ in tissue resistance, vessel penetration, comfort, treatment time and bruising. It also covers when each approach may be useful and what to consider when comparing them.
Key Takeaways
- Compare the blunt, flexible cannula with the short, sharp needle to understand how each reaches and delivers filler.
- Consider how the treatment area and desired placement affect comfort, bruising and the number of entry points.
- Don’t assume a cannula cannot penetrate a vessel; gauge and injection direction also matter.
- Use tissue resistance and the intended level of precision to understand why practitioners may choose one instrument or use both.
Potential effects on discomfort, treatment time and bruising
Before treatment, patients can discuss the target area and the planned injection approach. During treatment, filler is delivered with a needle or cannula. Afterwards, tenderness, swelling or bruising may occur.
Both approaches penetrate the skin, but cannula treatment starts with an entry point made by a needle. The practitioner then passes the blunt cannula through that opening. Rather than making repeated punctures, the cannula moves beneath the skin from one access point.
Discomfort and patient experience
Discomfort can depend on the number of punctures and the treatment area. A cannula may reach several nearby points through one entry, reducing the number of separate skin penetrations. A needle may require repeated punctures to distribute filler across the same area. Patients can therefore experience the approaches differently, even when similar areas are treated.
Treatment time
A cannula can reach several points from one entry, which may streamline filler delivery across a broader area. A needle may involve more punctures to cover that area. However, treatment time also depends on the planned placement and the practitioner’s technique. Fewer entry points alone do not determine how long an appointment will take.
Bruising and vessel-piercing risks
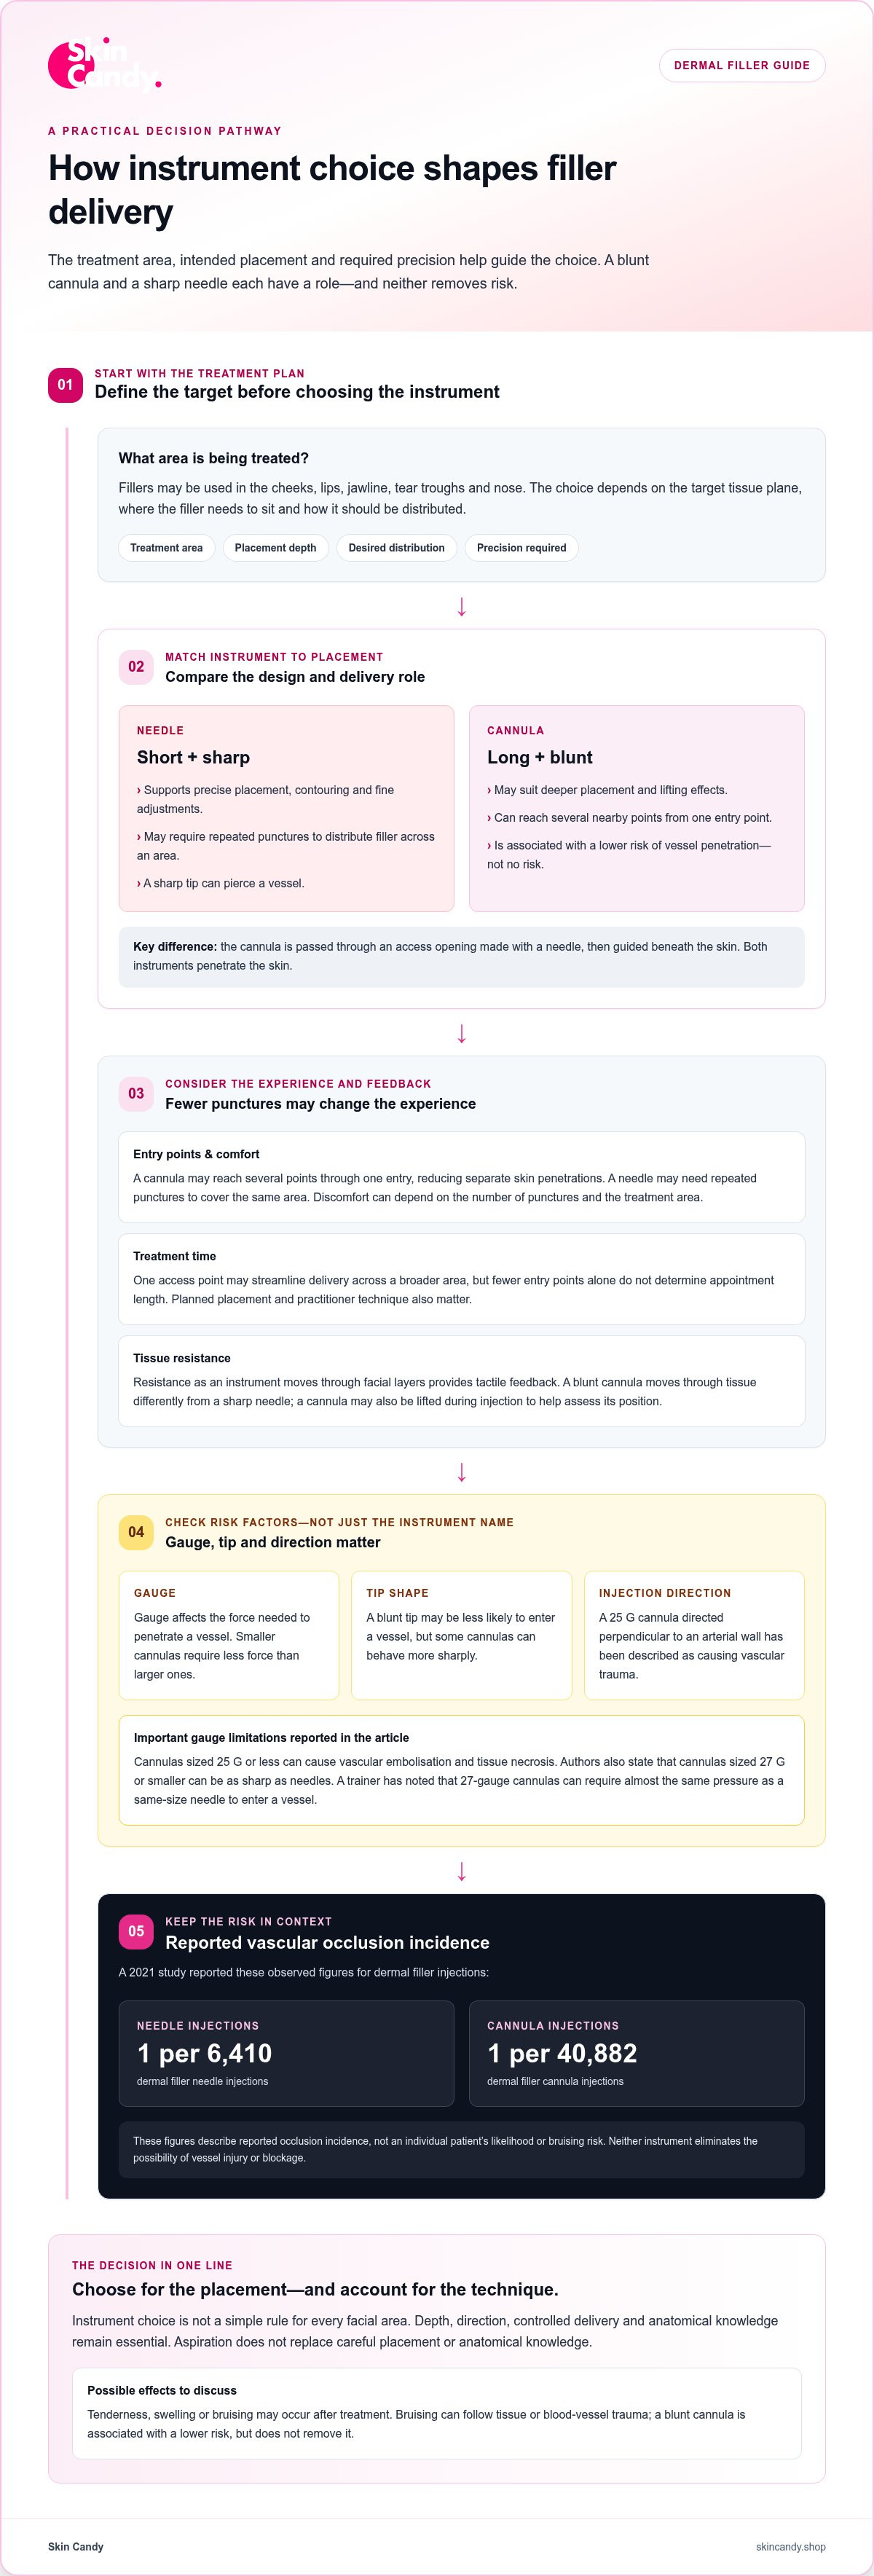
Bruising can follow tissue or blood-vessel trauma. A sharp needle can pierce a vessel, whilst a blunt cannula is associated with a lower risk of vessel penetration and bruising. Neither instrument removes the risk. The Authors of the 2021 study reported one vascular occlusion per 6,410 dermal filler needle injections. This figure describes occlusion incidence, not the likelihood of bruising for an individual patient.
| Instrument | Entry points | Potential patient experience | Vessel interaction |
|---|---|---|---|
| Needle | May require repeated punctures | More separate skin entries | Sharp tip can pierce vessels |
| Cannula | Can reach several areas from one entry | Fewer skin punctures | Blunt tip is associated with lower penetration risk |
Choose an approach based on the treatment area, planned distribution and desired placement, rather than comfort alone.
Using tissue resistance to guide injection
As an instrument moves through facial layers, tissue resistance provides tactile feedback. This can help guide placement, but the instrument and its direction also affect tissue trauma.
In the UK, safe practice relies on understanding facial anatomy, placement depth and injection technique. Accidental filler injection into a blood vessel can cause serious harm, including blindness, tissue necrosis or paralysis.
Fillers are used in areas including the cheeks, lips, jawline, tear troughs and nose. Depending on the area and intended placement, practitioners may use a cannula or a needle.
Tissue resistance during injection
A cannula can be lifted during injection to help assess its position within different tissue layers. Its blunt tip moves through tissue rather than cutting in the same way as a sharp needle, giving a different resistance profile. The Authors of the cited studies described vascular trauma caused by 25 G cannulas when the injection axis is perpendicular to the arterial wall.
Instrument choice and injection technique
Instrument choice depends on the target tissue plane and the precision required. Needles can support contouring and fine adjustments, but filler may be delivered across multiple layers. A cannula may suit deeper placement and lifting effects; some authors consider non-traumatic cannulas safer and less painful for these purposes. Neither instrument removes risk: direction, depth and controlled delivery remain essential.
One described needle technique uses a slow, continuous bolus in the supraperiosteal layer, with regular aspiration to check for vascular injury. Aspiration does not replace anatomical knowledge or careful placement. There is no simple rule that one instrument is right for every facial area.
For practitioners reviewing products for filler treatments, dermal filler options can be considered alongside the intended placement and injection technique.
Cannula gauge and vessel penetration
A cannula may reduce the chance of vessel penetration, but its gauge matters. It does not make vascular occlusion impossible: diameter, tip sharpness and injection direction all affect risk.
Vessel-blockage risk
A 2021 study reported one vascular occlusion per 40,882 dermal filler cannula injections. This figure describes observed incidence, not a guarantee for an individual treatment. A blunt tip can be less likely to enter a vessel than a sharp needle, which is one potential benefit of cannula use.
Risk depends on more than whether the instrument is called a cannula or a needle. Cannula gauge, tip shape and angle of travel matter too. A cannula directed perpendicular to an arterial wall can still cause trauma. Practitioners need to consider the route and target tissue, rather than assuming a blunt tip guarantees safety.
Cannula limitations
Gauge affects the force needed to penetrate a vessel. Smaller cannulas require less force than larger ones, and cannula size is significantly correlated with the force required. A narrow cannula may therefore offer a different mechanical barrier from a wider one.
There are important exceptions to the blunt-tip assumption. Cannulas sized 25 G or less can cause vascular embolisation and tissue necrosis. Authors also state that cannulas sized 27 G or smaller can be as sharp as needles. A trainer has noted that 27-gauge cannulas can require almost the same pressure as a same-size needle to enter a vessel.
Consider gauge alongside tip design and injection direction when selecting an instrument. A cannula may lower risk, but cannot eliminate vessel injury or blockage. The distinction is risk reduction, not risk elimination: a smaller or more pointed cannula may behave differently from a wider blunt one.
Cannula and needle design
The design of each instrument explains how it behaves during filler placement. Compare the tip, length and delivery opening, not just the instrument name.
In the UK, the instrument alone does not determine the cost of a filler treatment. The planned treatment and product also matter, so do not assume that one delivery method automatically costs more.
A dermal filler needle is short and sharp, allowing precise placement near the area where filler will be distributed. A cannula is longer, blunt and flexible. The practitioner creates an entry point with a sharp needle, then passes the cannula through it. The cannula vs needle for dermal fillers decision starts with how each instrument reaches the target.
Gauge is another design detail. Aesthetic injectors use needles and cannulas ranging from 30 gauge at the narrowest to 22 gauge at the widest. Gauge affects instrument diameter, while the treatment area and desired precision inform which design is suitable. Cannulas can be one to two inches long, depending on the area or precision required.
The delivery opening changes filler flow. A cannula’s port releases filler at a 90-degree angle to the instrument. A needle releases it at an angle closer to 10 degrees. This difference influences how the practitioner directs product into the chosen plane. It’s a key part of the cannula vs needle for dermal fillers comparison, beyond the contrast between blunt and sharp tips.
For example, a cannula can move through tissue to distribute filler across a broader area from one entry point. A needle can target a specific placement, which may help with contouring or fine adjustments. These are different delivery characteristics, not a guarantee that either instrument suits every treatment.
To compare the approaches, consider three details: the target area, the precision required and the intended distribution. This makes the design trade-off clearer than choosing by length or tip alone.
Review dermal filler products alongside the treatment requirements and intended placement.
Skin Candy: Lumi Meso
Skin Candy’s Lumi Meso is a separate product for clinics sourcing professional aesthetic products. It does not determine whether a cannula or needle is suitable for a dermal filler treatment. Keep the instrument choice tied to the intended placement and delivery technique.
Skin Candy also supplies Polynucleotides, Fat Dissolving Agents and Chemical Peels for clinic stock. These are distinct product categories, not substitutes for dermal fillers or injection instruments. Keeping the categories clear helps match purchases to their intended use.
To source Lumi Meso or other professional aesthetic products, contact Skin Candy or visit skincandy.shop.
Make your next product decision with confidence
Use the cannula-versus-needle comparison to frame a practical discussion about dermal filler placement, technique and clinic stock. Instrument choice is part of the treatment plan; sourcing products is a separate step. Keep the decisions distinct when reviewing your requirements.
Skin Candy supplies professional aesthetic products for your practice. Consider which product category fits your clinic’s planned treatments, then browse the options available from Skin Candy. A focused product discussion can help turn a general comparison into a clear procurement decision.
For the next step, contact Skin Candy to discuss your options. Bring your product requirements and intended use into the conversation, and choose what best fits your clinic’s needs. You’re ready to make an informed decision.
Frequently Asked Questions
What is a cannula?
A cannula is a long, flexible instrument with a blunt tip that delivers dermal filler beneath the skin. Unlike a sharp needle, it passes through an entry point created with a needle. Its flexibility lets the practitioner guide it along a planned route, potentially distributing filler across connected areas without a separate entry for each point.
What is the difference between a cannula and a needle for dermal fillers?
A needle has a sharp tip and offers a precise point of delivery. A cannula has a blunt tip and can travel beneath the skin from an entry point. The delivery openings differ too: filler exits a cannula port at a right angle, while filler from a needle exits at an angle closer to the instrument’s direction.
What are the advantages and disadvantages of cannula versus needle filler injections?
A cannula can reach several nearby areas through one entry, potentially reducing separate punctures. Its flexibility and blunt tip also affect how it moves through tissue. A needle offers precise placement and can support contouring or fine adjustments. Cannula use is technically more difficult and is not automatically suitable for every placement. The intended result and target tissue guide the choice.
How do cannula and needle filler techniques differ in pain, bruising and recovery time?
When filler is distributed across an area, cannula treatment may involve fewer punctures, which can affect discomfort. A needle may require repeated skin entries. Either approach can cause bruising or swelling through tissue trauma. Recovery depends on the treatment area and the extent of the tissue response, so the instrument alone cannot provide a reliable timetable.
Which technique has a lower risk of bruising, vascular occlusion or other complications?
Cannulas are generally associated with lower bruising and vessel-penetration risk, but neither method eliminates complications. Gauge, tip shape, direction and placement all matter. Vascular occlusion is not the same as surface bruising: it involves a blocked blood vessel and can have serious consequences. A blunt tip is no guarantee against vessel injury.
How do clinicians choose between a cannula and a needle for dermal fillers?
Clinicians weigh the facial area, target tissue plane, required precision and intended filler distribution. A needle may suit a focused contour adjustment, while a cannula can help distribute product across connected tissue from one entry point. The practitioner’s understanding of facial anatomy and control of placement matter too. Both instruments may be used in one treatment when the plan calls for different delivery approaches.


